ED Management
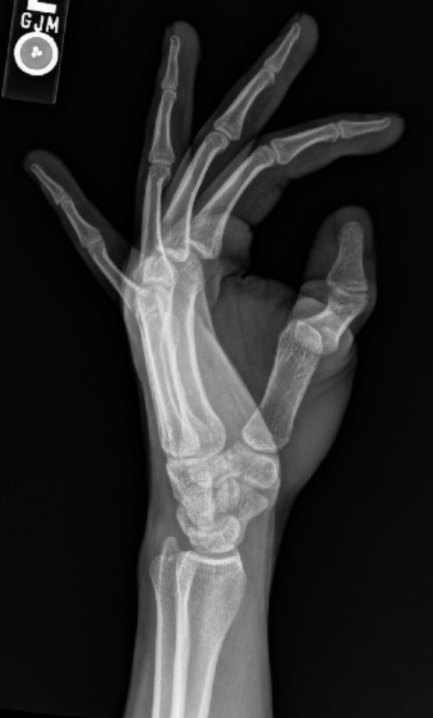
A digital nerve block can be used to facilitate closed reduction attempts. To reduce a dorsal dislocation, the wrist and MCP are held in flexion, with dorsal pressure over the proximal phalanx. Flexing the joint during reduction may be helpful. Different from interphalangeal dislocations, longitudinal traction should be avoided to prevent further injury to the volar plate.
Delayed reduction may result in chronic stiffness, pain, arthritis, deformity, or edema, resulting in decreased hand function.
MCP dislocations unable to be reduced in the ED require operative intervention. Avoid repeated reduction attempts as this may further injure the volar plate. There is high likelihood for volar plate entrapment in irreducible dislocations. A complex dislocation occurs when the metacarpal head ruptures the volar plate. Volar dislocations are rare and typically require operative repair.
After reduction:
- Document associated ligamentous injury by repeat physical exam, testing for laxity with abduction or adduction while the joint is in flexion.
- The joint should be immobilized in flexion for 3-6 weeks, followed by buddy taping.